







Expo
view channel
view channel
view channel
view channel
view channel
view channel
view channel
view channel
view channel
Clinical Chem.Molecular DiagnosticsHematologyImmunology
PathologyTechnologyIndustry
Events
Webinars

- Global Survey Underscores Need to Standardize Bone Biomarker Testing
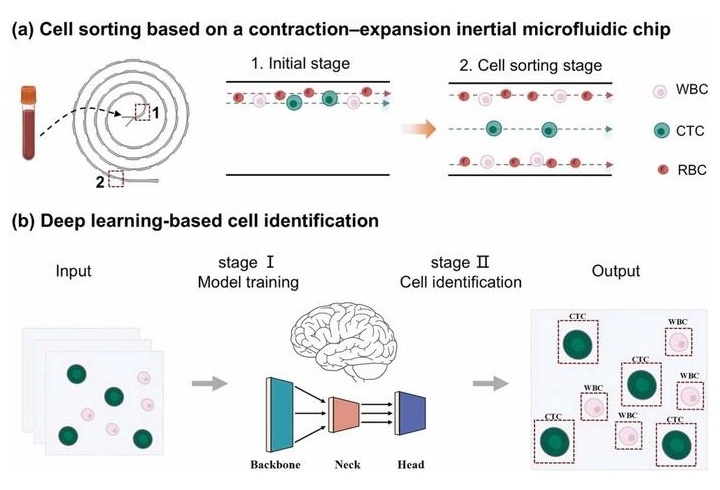
- Label-Free Platform Combines Microfluidics and AI for Circulating Tumor Cell Analysis
- Rapid D-Dimer Assay Supports Exclusion and Monitoring of Serious Clotting Conditions
- Noninvasive Earwax Test Aims to Detect Meniere’s Disease
- Point-of-Care Blood Test Could Speed Treatment Decisions in Acute Stroke
- Urine-Based RNA Improves Bladder Cancer Detection and Monitoring
- Blood RNA Panel Predicts Lung Cancer Risk Years Before Diagnosis
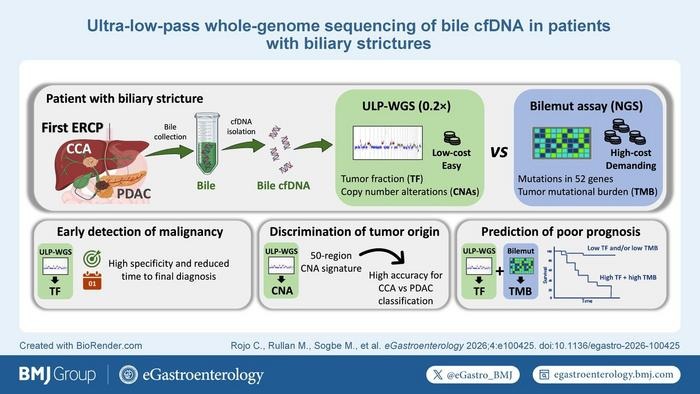
- Bile DNA Testing Detects Tumor Signals Before Conventional Cancer Diagnosis
- New Blood Test Could Help Predict Severe Scoliosis in Adolescents
- Blood-Based Test Broadens Colorectal Cancer Screening Options
- Updated Ferritin Thresholds Improve Detection of Iron Deficiency
- New Automated Hemostasis Systems Become Available Across US Laboratories
- Variation in AML Residual Disease Testing Prompts Push for Standardization
- Hidden Molecular Mechanism Behind HIT Blood-Clotting Disorder Revealed
- Borderline Anemia May Carry Higher Risk Than Current Thresholds Suggest
- Blood Test Differentiates Bacterial and Viral Infections in Febrile Infants
- New Autoantibody Test Targets Pre-Symptomatic Type 1 Diabetes Screening
- HIV Monitoring Strategy Uses Drug Levels to Guide Resistance Testing
- Werfen Expands Automated APS Testing with FDA-Cleared and CE-Marked IgA Reagent
- Blood Biomarker May Predict Colitis Risk in Checkpoint Inhibitor Therapy
- One-Hour Molecular Panel Expands Bloodstream Infection Testing for Gram-Negative Pathogens
- FDA Clears Rapid Phenotypic Antimicrobial Susceptibility System for Positive Blood Cultures
- New Urine Test Expands Mycotoxin Analysis to 31 Markers for Broader Exposure Assessment
- Collaboration Targets Blood-Based Ebola Detection Outside Central Laboratories
- Study Finds Frequent Overlap in Antibodies to Lyme and Other Tick-Borne Pathogens
- Laser-Enhanced Assay Boosts Sensitivity for Colorectal Cancer Biomarker Detection
- New Automation Workflow Streamlines NGS Library Preparation for High-Volume Labs
- ADLM Calls for CLIA Updates to Support Safe AI Use in Laboratory Medicine
- Multimodal AI Framework Aims to Guide Cancer Immunotherapy Decisions
- New Multipurpose Centrifuge Combines High Capacity with Sustainable Cooling
- Mayo Clinic Laboratories and Pathology Asia Expand Genomic Testing Across Asia-Pacific
- New UK Collaboration Expands Access to Integrated Alzheimer’s Diagnostic Testing
- Multi-Cancer Early Detection Test Wins FDA Panel Backing for Approval
- Siemens Healthineers and Novo Collaborate to Expand Access to Noninvasive Liver Testing
- Mayo Clinic and Thermo Fisher Launch Multi-Omics Venture to Identify Early Disease Signals
- Researchers Classify 108 Lysosomal Disorders in Updated Diagnostic Framework
- New Autoantibody Target Identified in Neuromyelitis Optica Spectrum Disorder
- New Gene-Disease Link May Help Diagnose Rare Neurodevelopmental Disorders
- Researchers Identify Shared Molecular Networks Behind Fatigue-Related Illnesses
- New Immune Target Could Support More Precise High Blood Pressure Treatment
- Genomic Classifier Predicts Benefit From Adding Hormone Therapy to Salvage Prostate Radiation
- New AI Model Maps Where Glioblastoma Could Return After Surgery
- Multimodal AI Supports Prostate Cancer Risk Assessment Across Diverse Cohorts
- Simple Test Could Reduce the Need for Invasive Uterine Cancer Checks
- Tumor Blood Vessel Features May Help Predict Colorectal Cancer Survival
 Expo
- Global Survey Underscores Need to Standardize Bone Biomarker Testing
- Label-Free Platform Combines Microfluidics and AI for Circulating Tumor Cell Analysis
- Rapid D-Dimer Assay Supports Exclusion and Monitoring of Serious Clotting Conditions
- Noninvasive Earwax Test Aims to Detect Meniere’s Disease
- Point-of-Care Blood Test Could Speed Treatment Decisions in Acute Stroke
- Urine-Based RNA Improves Bladder Cancer Detection and Monitoring
- Blood RNA Panel Predicts Lung Cancer Risk Years Before Diagnosis
- Bile DNA Testing Detects Tumor Signals Before Conventional Cancer Diagnosis
- New Blood Test Could Help Predict Severe Scoliosis in Adolescents
- Blood-Based Test Broadens Colorectal Cancer Screening Options
- Updated Ferritin Thresholds Improve Detection of Iron Deficiency
- New Automated Hemostasis Systems Become Available Across US Laboratories
- Variation in AML Residual Disease Testing Prompts Push for Standardization
- Hidden Molecular Mechanism Behind HIT Blood-Clotting Disorder Revealed
- Borderline Anemia May Carry Higher Risk Than Current Thresholds Suggest
- Blood Test Differentiates Bacterial and Viral Infections in Febrile Infants
- New Autoantibody Test Targets Pre-Symptomatic Type 1 Diabetes Screening
- HIV Monitoring Strategy Uses Drug Levels to Guide Resistance Testing
- Werfen Expands Automated APS Testing with FDA-Cleared and CE-Marked IgA Reagent
- Blood Biomarker May Predict Colitis Risk in Checkpoint Inhibitor Therapy
- One-Hour Molecular Panel Expands Bloodstream Infection Testing for Gram-Negative Pathogens
- FDA Clears Rapid Phenotypic Antimicrobial Susceptibility System for Positive Blood Cultures
- New Urine Test Expands Mycotoxin Analysis to 31 Markers for Broader Exposure Assessment
- Collaboration Targets Blood-Based Ebola Detection Outside Central Laboratories
- Study Finds Frequent Overlap in Antibodies to Lyme and Other Tick-Borne Pathogens
- Laser-Enhanced Assay Boosts Sensitivity for Colorectal Cancer Biomarker Detection
- New Automation Workflow Streamlines NGS Library Preparation for High-Volume Labs
- ADLM Calls for CLIA Updates to Support Safe AI Use in Laboratory Medicine
- Multimodal AI Framework Aims to Guide Cancer Immunotherapy Decisions
- New Multipurpose Centrifuge Combines High Capacity with Sustainable Cooling
- Mayo Clinic Laboratories and Pathology Asia Expand Genomic Testing Across Asia-Pacific
- New UK Collaboration Expands Access to Integrated Alzheimer’s Diagnostic Testing
- Multi-Cancer Early Detection Test Wins FDA Panel Backing for Approval
- Siemens Healthineers and Novo Collaborate to Expand Access to Noninvasive Liver Testing
- Mayo Clinic and Thermo Fisher Launch Multi-Omics Venture to Identify Early Disease Signals
- Researchers Classify 108 Lysosomal Disorders in Updated Diagnostic Framework
- New Autoantibody Target Identified in Neuromyelitis Optica Spectrum Disorder
- New Gene-Disease Link May Help Diagnose Rare Neurodevelopmental Disorders
- Researchers Identify Shared Molecular Networks Behind Fatigue-Related Illnesses
- New Immune Target Could Support More Precise High Blood Pressure Treatment
- Genomic Classifier Predicts Benefit From Adding Hormone Therapy to Salvage Prostate Radiation
- New AI Model Maps Where Glioblastoma Could Return After Surgery
- Multimodal AI Supports Prostate Cancer Risk Assessment Across Diverse Cohorts
- Simple Test Could Reduce the Need for Invasive Uterine Cancer Checks
- Tumor Blood Vessel Features May Help Predict Colorectal Cancer Survival




























 Client Login
